

HPB Academy

Case 1
Lorem ipsum dolor sit amet, consectetur adipiscing elit. Sed do eiusmod tempor incididunt ut labore et dolore magna aliqua. Ut enim ad minim veniam, quis nostrud exercitation ullamco laboris nisi ut aliquip ex ea commodo consequat. Duis aute irure dolor in reprehenderit in voluptate velit esse cillum dolore eu fugiat nulla pariatur. Excepteur sint occaecat cupidatat non proident, sunt in culpa qui officia deserunt mollit anim id est

Case 2
Lorem ipsum dolor sit amet, consectetur adipiscing elit. Sed do eiusmod tempor incididunt ut labore et dolore magna aliqua. Ut enim ad minim veniam, quis nostrud exercitation ullamco laboris nisi ut aliquip ex ea commodo consequat. Duis aute irure dolor in reprehenderit in voluptate velit esse cillum dolore eu fugiat nulla pariatur. Excepteur sint occaecat cupidatat non proident, sunt in culpa qui officia deserunt mollit anim id est
See DetailLeft Hepatectomy [case 1]
Introduction
Clinical History
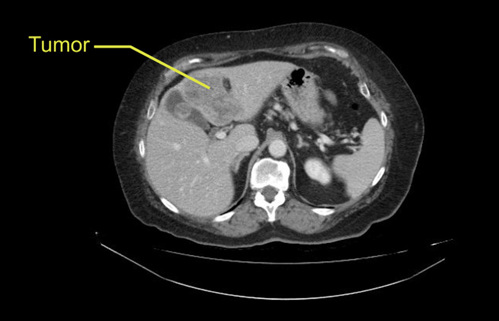
A 71-year old woman was diagnosed with advanced rectal cancer. She underwent neo-adjuvant chemoradiation and had an APR (abdominoperineal resection) followed by 6 cycles of FOLFOX chemotherapy. In follow-up, she had a rising level of CEA (carcinoembryonic antigen) and a CT scan showed a single liver metastasis in the left lobe. Our plan for her is to do a formal left hepatectomy.
Left Hepatectomy [case 1]
Imaging Analysis
Look through the patient's CT scan to identify any areas of concern for the necessary procedure.
Insert Image Sequence here
Left Hepatectomy [case 1]
Surgeon's Impressions
Operating surgeon: Dr. Moulton
- Critical imaging findings:
- Portal vein trifurcation
- Replaced left hepatic artery
- Left hepatic vein branch
- Preserving caudate inflow and bile duct
- Left bile duct
Consulting surgeon: Dr. Gallinger
- Critical imaging findings:
- Tumor proximity to MHV
- Tumor proximity to gallbladder
- Portal vein
- Left bile duct
Watch the following videos from the operation to see some of the key moments in the case.
Watch the following video for the operating surgeon's summary of the case.
Key points from this case
- Portal vein trifurcations: look out for anatomy of the portal vein and be mindful of any variations in anatomy.
- Bile duct: be careful of tumor margins, especially with anterior tumors in Segment 4.
- Gallbladder: when tumor margins are close to the gallbladder, routine cholecystectomy is not appropriate.
The issues that the surgeons collectively identified preoperatively:
- Tumor proximity to gallbladder
- Replaced left hepatic artery
- Portal vein trifurcation
- Left bile duct and preserving caudate biliary drainage
- Tumor proximity to middle hepatic vein
- Left hepatic vein branching
The first 4 issues were demonstrated in the intraoperative videos. Intraoperative ultrasound confirmed that the tumor was not too close to the middle hepatic vein. We were able to take it outside the liver and divide its small crossing branches during parenchymal transection, preserving the middle hepatic vein. We took the left hepatic vein outside the liver as usual.