Whipple with vascular resection and reconstruction [Case 23]
Introduction
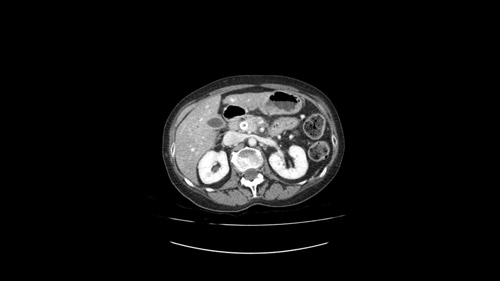
A 62 year old woman initially presented with jaundice 6-months ago. She was found to have an ill-defined pancreatic adenocarcinoma in the head of the pancreas measuring 3.7 x 2.5cm. The mass appears to involve over 180° of the PV-SMV for a length of 2.5cm, with the SMV almost completely occluded. There is also involvement of the SMA (less than 180°). The lesion was deemed borderline resectable with possibility of vascular reconstruction.
She received a metal stent in the common bile duct to relieve the jaundice and then underwent chemoradiation. The pancreatic lesion has decreased slightly in size, to 2.4cm. There are some collaterals likely due to occlusion of the SMV. The patient has developed moderate to severe steatosis, but her biliary dilatation and pancreas is stable. The common hepatic and celiac artery do not appear to be involved. There is dilatation of the pancreatic duct upstream of the lesion. Some peri-pancreatic nodes up to 0.5cm are seen. Her liver parenchymal changes are likely a result of inflammation from dilatation and biliary stenting.
Our plan is to prepare for a Whipple operation (pancreaticoduodenectomy) with vascular reconsctruction.
Whipple with vascular resection and reconstruction [Case 23]
Imaging Analysis
Look through the patient's CT scan to identify any areas of concern for the necessary procedure.
Surgeon's Impressions
Watch the following videos of the surgeons preoperative plans for the case. Compare their findings with your own analysis.
OR Footage
Summary of surgeons' findings and slowing down moments:
Operating surgeon, Dr. Moulton
Slowing down moments:
- Laparotomy
- Kocherization of duodenum
- Left renal vein harvest for SMV reconstruction
- Pancreatic tunnel dissection
- Replaced right hepatic artery
- Hepatic duct margin
- Gastrectomy and jejunum
- Possible SMA resection
- Reconstruction
Operating surgeon, Dr. McGilvray
Critical planned moments:
- PV-SMV resection, reconstruction
- SMA resection; primary sleeve / interposition graft
- Assess SMA, SMV
- Divide pancreas left of SMA
- Early control of SMA; aortic, mesenteric approach
Watch the following videos from the operation to see some of the key moments in the case.
Post-op Debrief
Watch the following videos for the operating surgeon's summary of the case.
Key points from this case
- When considering vascular reconstruction, especially in patients with aberrant arterial anatomy, plan ahead for possible vein harvest(s) and assess lengths of vascular structures to ensure appropriate tension and blood flow.
- Tumor obstruction of a major vascular structure such as the superior mesenteric vein can result in unanticipated collateral vessels; coupled with tissue changes from radiation treatment may lead to a more challenging dissection than usual.
The issues that the surgeons collectively identified preoperatively:
- Kocherization, Cattell-Braasch
- Left renal vein harvest for SMV reconstruction
- Pancreatic tunnel to the left of SMA
- Replaced RHA
- Hepatic duct margin
- Gastrectomy, jejunum
- Likely SMA resection
- Assess and control SMA, SMV
- Reconstruction