Laparoscopic liver wedge resection [Case 19]
Introduction
The patient is a 60-year old man with Hepatitis C. He was recently found to have a single mass, suspected HCC in Segment 6 of his liver. His bilirubin and blood count is normal. There is no evidence of portal hypertension. Our plan for him is to do a laparoscopic Sg5-6 wedge resection.
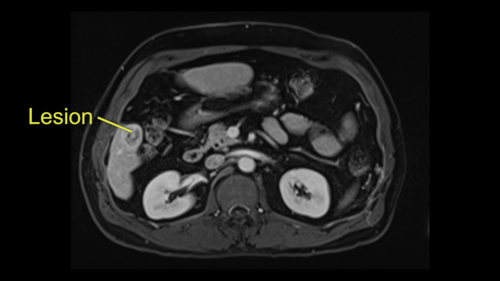
Laparoscopic liver wedge resection [Case 19]
Imaging Analysis
Look through the patient's CT scan to identify any areas of concern for the necessary procedure.
Laparoscopic liver wedge resection [Case 19]
Surgeon's Impressions
Watch the following videos of the surgeons preoperative plans for the case. Compare their findings with your own analysis.
OR Footage
Summary of surgeons' findings and slowing down moments:
Dr. Sapisochin's patient-specific moments:
- Rule out portal hypertension, ascites, splenomegaly
- No decompensation
- Laparoscopic Sg6 Wedge resection
- Proximity of lesion to colon, no invasion
- Peripheral lesion away from portal structures
- Plan for Pringle maneuver
Dr. McGilvray's patient-specific moments:
- Left-sided hypertrophy, right-sided atrophy
- Laparoscopic peripheral Sg 5-6 Wedge resection
- Reflect colon away from liver
- Two plane transection approach
- Plan for Pringle maneuver
Watch the following videos from the operation to see some of the key moments in the case.
Watch the following video for the operating surgeon's summary of the case.
Key points from this case
- Be prepared in setting up a Pringle maneuver early on, especially in patients with cirrhosis as often times the degree of cirrhosis can be greater than anticipated and minimizing blood loss is a concern for a liver that is particularly fibrotic.
- Keep in mind that even though the lesion is superficial, the transection surface may be greater than appears.
The issues that the surgeons collectively identified preoperatively:
- Left-sided hypertrophy, right-sided atrophy
- Proximity of tumor to colon, no invasion
- Determining transection plane approach
- Plan for Pringle maneuver
- Rule out portal hypertension
- Peripheral lesion, Sg5-6 wedge resection
The issues were demonstrated in the intraoperative videos. So we just finished. Not many surprises. I mean I was a bit impressed at how cirrhotic the liver was and actually when we took some adhesions on the gallbladder, there were some small varices there. I think it’s going to be okay. We did a pretty limited resection. The tumor was pretty exophytic as we anticipated. It was actually not stuck at all at the colon. We ended up doing a Segment 6 resection. We Pringled for around 25 minutes. Blood loss was minimal even though with a cirrhotic patient it’s sometimes difficult for the liver to really open up because they’re so fibrotic. We used both the CUSA and the Harmonic and there was no real problems. As I mentioned before surgery, I really like to Pringle these patients. I think small intermittent Pringle helps with blood loss especially in these cirrhotic patients in laparoscopic surgery to be able to see the planes even though this case was a little bit bloodier than I anticipated and we couldn’t really see the structures very well but I think the blood loss was minimal and the Pringle helped. Otherwise I think not many more teaching points. I think that was the key point in this case.